Clinical negligence costs need careful handling from the beginning of the claim.
These are often expert-heavy, evidence-heavy and procedurally demanding files. A weak costs budget, poor assumptions, unclear phase allocation or badly prepared bill can create serious problems later.
DMD Costs supports claimant solicitor firms with clinical negligence costs drafting, budgeting and negotiation. We assist with Precedent H, costs budgets, budget assumptions, bills of costs, Precedent S, Points of Dispute, Replies and detailed assessment preparation, on claims of every value, from a few thousand pounds to several million, including complex claims such as birth and brain injury. If a bill goes to a contested hearing, we arrange the advocate (counsel or a Costs Lawyer) and prepare the papers.
Our focus is to protect the value of the work properly done on the file.
Costs Support for Claimant Clinical Negligence Firms
Clinical negligence claims often involve complex liability and causation issues, multiple experts, medical record review, conferences, settlement strategy and careful budgeting. The costs work needs to reflect that. We help claimant firms with:
- Precedent H costs budgets;
- budget assumptions;
- budget discussion reports;
- CCMC preparation support;
- bills of costs;
- electronic bills;
- Precedent S;
- N260 schedules;
- Points of Dispute;
- Replies to Points of Dispute;
- detailed assessment preparation;
- costs negotiation;
- hourly rate disputes;
- expert fee disputes;
- proportionality arguments;
- phase-by-phase analysis.
Why Clinical Negligence Costs Are Different
Clinical negligence files are rarely straightforward. Even where damages settle, the work required can be substantial. A typical clinical negligence file may involve:
- medical records;
- chronology preparation;
- breach of duty evidence;
- causation evidence;
- condition and prognosis evidence;
- multiple expert disciplines;
- conferences with counsel;
- liability response review;
- Part 36 strategy;
- quantum evidence;
- witness evidence;
- settlement negotiation;
- costs budgeting;
- budget variation issues;
- detailed assessment.
That work needs to be properly reflected in the costs documents. A generic bill or weak budget does not do justice to the file.
Precedent H Costs Budgets
A clinical negligence costs budget should not be treated as a form-filling exercise. The budget can shape recovery for the rest of the claim. If the assumptions are too thin, the phases are unrealistic or expert costs are not properly explained, the claimant may face difficulty later. DMD Costs assists with Precedent H preparation, including:
- phase-by-phase budgeting;
- assumptions;
- incurred costs review;
- estimated costs;
- expert evidence phases;
- disclosure assumptions;
- witness evidence assumptions;
- trial preparation;
- ADR and settlement assumptions;
- counsel and expert fee presentation;
- proportionality review.
The aim is to prepare a budget that is realistic, defensible and properly connected to the litigation plan. Our guide to the costs forms and precedents sets out Precedent H alongside Precedent R, the budget discussion report, and Precedent T, the budget variation.
Costs management applies automatically to Part 7 multi-track claims, but not to claims stated at £10 million or more or, in proceedings begun on or after 6 April 2016, to claims made by or on behalf of a child; the court can still order budgets in those cases (CPR 3.12 and 3.13), and Practice Direction 3D para 2(f) names clinical negligence claims of £10 million or more as cases where that may be particularly appropriate. In Fuschillo v Johnson & Johnson (No 2) the High Court relied on that paragraph to order budgeting: costs updates tell the court what has already been spent, while budgeting gives it the chance to control expenditure before it is incurred. Once a costs management order is made, the court controls the parties’ budgets in respect of recoverable costs (CPR 3.15), and on a standard basis assessment it will not depart from the last approved or agreed budget for each phase without good reason (CPR 3.18).
Budget Assumptions That Survive the CCMC
Assumptions matter. A budget without proper assumptions gives the other side room to argue that the figures are excessive or unsupported. In clinical negligence claims, assumptions should usually address:
- the number of expert disciplines;
- whether breach and causation are disputed;
- likely medical record volume;
- disclosure scope;
- witness evidence;
- conferences;
- counsel input;
- liability response;
- Part 35 questions;
- joint statements;
- ADR;
- trial length;
- settlement stage;
- complexity of quantum.
The assumptions should be clear enough to justify the budget without overcomplicating the document. Practice Direction 3D asks only for those that significantly affect the level of costs, such as the duration of the proceedings, the number of experts and witnesses, or the number of interim applications envisaged (PD 3D para 10(a)).
Costs Budgeting and Proportionality
Clinical negligence claims can involve significant costs, especially where expert evidence is required across multiple disciplines. The paying party may argue that the budget is disproportionate. A strong budget should explain why the work is needed and how it relates to the issues in dispute. We look at:
- damages value;
- complexity;
- breach issues;
- causation issues;
- expert evidence;
- defendant conduct;
- settlement prospects;
- proportionality;
- phase allocation;
- risk areas;
- future work.
The budget must be ambitious enough to protect recovery but realistic enough to survive challenge.
Budget Variations
If the litigation changes significantly, the budget may need to be revised: a party must revise its budgeted costs upwards or downwards where significant developments warrant it, and submit the revision promptly, using Precedent T (CPR 3.15A). Clinical negligence claims can develop quickly, and an amended case that changes the issues, or new evidence raising an expert issue nobody could have anticipated, may qualify. Work that was foreseeable when the budget was approved, such as further expert reports the case was always likely to need, is not a significant development, however much of it there is (Bassey v Whittaker). We can assist with budget variation support where appropriate, including:
- reviewing the existing budget;
- identifying significant developments;
- preparing revised figures;
- updating assumptions;
- explaining the change;
- preparing for negotiation;
- assisting with the costs position.
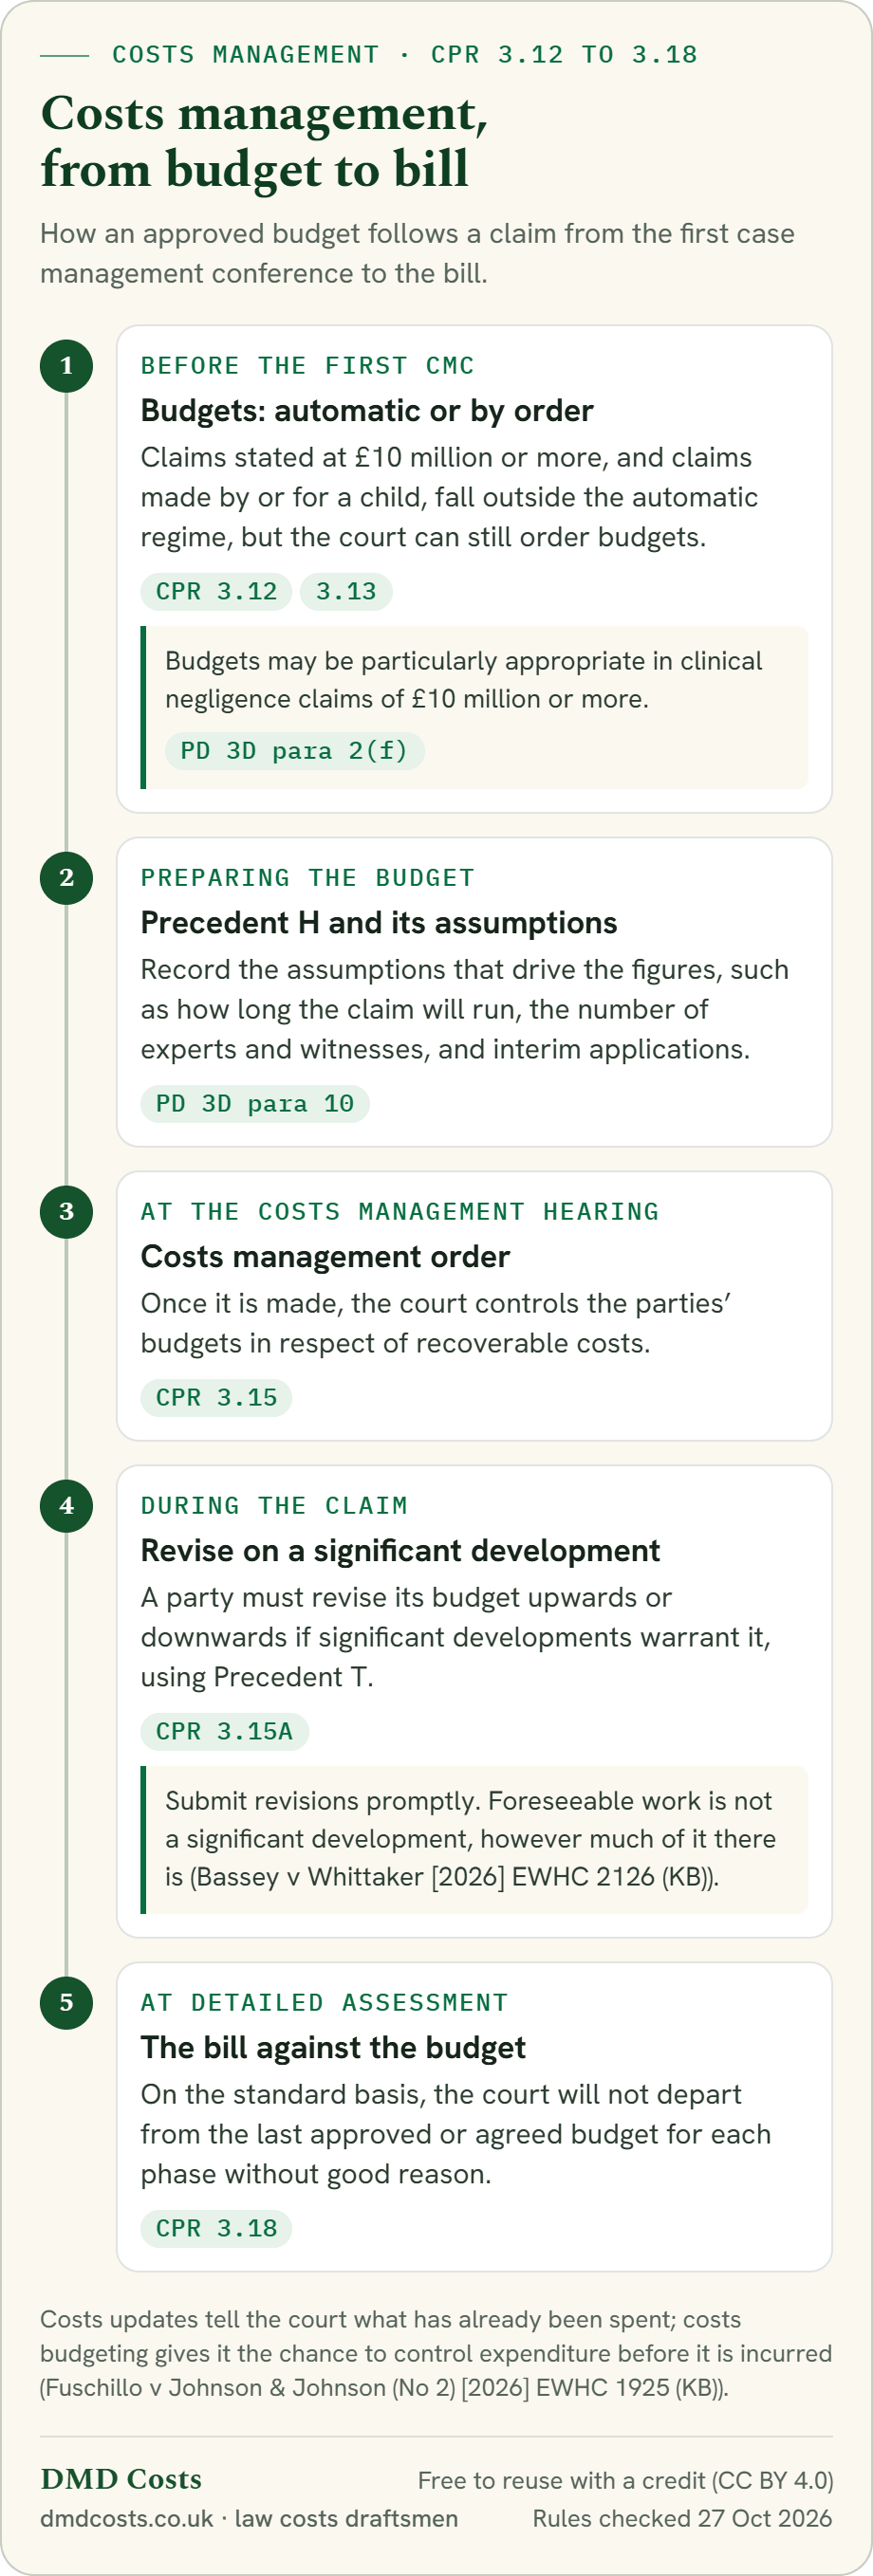
Claims stated at £10 million or more, and claims made by or for a child, fall outside automatic costs management (CPR 3.12), but the court can still order budgets (CPR 3.13), and PD 3D para 2(f) names clinical negligence claims of £10 million or more as cases where budgeting may be particularly appropriate. After a costs management order, the court controls the parties’ budgets for recoverable costs (CPR 3.15). A party must revise its budget up or down if significant developments warrant it, on Precedent T (CPR 3.15A). On a standard basis assessment, the court departs from the last approved or agreed budget only for good reason (CPR 3.18).
Free to reuse under CC BY 4.0: credit “DMD Costs (dmdcosts.co.uk)” and link to this page. Download the PNG.
Text version of this diagram
How an approved budget follows a claim from the first case management conference to the bill.
- Before the first CMC: Budgets: automatic or by order. Claims stated at £10 million or more, and claims made by or for a child, fall outside the automatic regime, but the court can still order budgets (CPR 3.12, 3.13).
- Budgets may be particularly appropriate in clinical negligence claims of £10 million or more (PD 3D para 2(f)).
- Preparing the budget: Precedent H and its assumptions. Record the assumptions that drive the figures, such as how long the claim will run, the number of experts and witnesses, and interim applications (PD 3D para 10).
- At the costs management hearing: Costs management order. Once it is made, the court controls the parties’ budgets in respect of recoverable costs (CPR 3.15).
- During the claim: Revise on a significant development. A party must revise its budget upwards or downwards if significant developments warrant it, using Precedent T (CPR 3.15A).
- Submit revisions promptly. Foreseeable work is not a significant development, however much of it there is (Bassey v Whittaker [2026] EWHC 2126 (KB)).
- At detailed assessment: The bill against the budget. On the standard basis, the court will not depart from the last approved or agreed budget for each phase without good reason (CPR 3.18).
Costs updates tell the court what has already been spent; costs budgeting gives it the chance to control expenditure before it is incurred (Fuschillo v Johnson & Johnson (No 2) [2026] EWHC 1925 (KB)).
Rules checked 27 October 2026.
Clinical Negligence Bills of Costs
At the end of the claim, the bill needs to match the work actually done and the budget position. We prepare clinical negligence bills that identify:
- the case background;
- liability and causation issues;
- expert evidence;
- counsel involvement;
- settlement history;
- budget phases;
- incurred and budgeted costs;
- fee earner details;
- hourly rates;
- disbursements;
- VAT;
- proportionality;
- detailed assessment readiness.
A clinical negligence bill should not read like a standard low-value personal injury bill. It should reflect the complexity of the medical and procedural work.
Precedent S Electronic Bills
Where an electronic bill is required, we prepare Precedent S for clinical negligence matters. We focus on:
- correct phase coding;
- budget alignment;
- incurred and estimated costs;
- fee earner grades;
- hourly rates;
- medical records work;
- expert evidence;
- counsel fees;
- conferences;
- offers and settlement;
- disbursements;
- VAT;
- clear descriptions.
Clinical negligence electronic bills need to be precise. Errors in phase coding or poor descriptions can create unnecessary disputes.
Points of Dispute and Replies
Clinical negligence costs are often heavily challenged. Paying parties may attack:
- proportionality;
- hourly rates;
- senior fee earner time;
- medical records review;
- expert fees;
- counsel’s fees;
- conferences;
- duplication;
- budget overspend;
- incurred costs;
- estimated costs;
- trial preparation;
- settlement work;
- Part 36 advice.
We prepare Replies that deal with the actual issues raised and explain why the work was reasonably incurred. The aim is to reduce the dispute, protect the strong parts of the bill and move the matter towards settlement or assessment. Our guide to clinical negligence Points of Dispute and detailed assessment covers the timetable, the challenges paying parties usually make and worked examples of Replies.
When the notice of commencement goes out, our free N252 builder fills in the form; if no Points of Dispute arrive in time, the N254 builder requests the default costs certificate. Every free tool, with plain answers to the questions fee earners ask, is on our costs help page.
Expert Fee Disputes
Expert evidence is often central to clinical negligence litigation. The paying party may argue that expert fees are excessive, that too many experts were used, or that the work went beyond what was reasonable. We help present expert fees clearly by linking them to:
- the pleaded issues;
- breach of duty;
- causation;
- condition and prognosis;
- quantum;
- Part 35 questions;
- joint statements;
- conferences;
- settlement.
Expert fees should not be left as unexplained disbursements. They should be properly connected to the work required on the claim.
ATE Premiums and Counsel’s Fees
After-the-event insurance premiums are generally not recoverable from the paying party for policies taken out since 1 April 2013. Clinical negligence is the exception: where the claim for damages is worth more than £1,000, the part of the premium that insures against the cost of expert reports on liability or causation can still be recovered (section 58C of the Courts and Legal Services Act 1990 and regulation 3 of the Recovery of Costs Insurance Premiums in Clinical Negligence Proceedings (No. 2) Regulations 2013). Paying parties often dispute how much of the premium relates to those reports, so the bill should show the policy and how the recoverable part of the premium was worked out.
Counsel’s fees are tested for necessity and amount: conferences, advices, the number of counsel and the brief fee. We show what each piece of counsel’s work did for the issues in the claim, alongside the expert evidence it relied on.
NHS Resolution and Payments on Account
In claims against NHS bodies in England, the bill is usually examined by NHS Resolution, which handles clinical negligence claims on their behalf, or by the panel solicitors and costs specialists it instructs. Our note on NHS Resolution’s latest annual figures looks at what they mean for claimant firms.
Costs that take months to settle are a cash-flow problem. Where the court orders costs to be paid subject to detailed assessment, it will order a reasonable sum on account unless there is good reason not to (CPR 44.2(8)), and there is no fixed percentage: see how the court set £550,000 on account of £1.2 million of costs in Cleveland Potash. We prepare the costs information behind an application or a request for an interim payment, so the firm is not left waiting for the final figure.
N260 and Interim Costs
Clinical negligence claims often involve interim hearings, applications and case management hearings. We can assist with N260 schedules and summary assessment preparation. We consider:
- correct hourly rates;
- fee earner grades;
- hearing preparation;
- counsel fees;
- application work;
- proportionality;
- VAT;
- disbursements;
- attendance time.
A clean N260 can prevent avoidable reductions at hearing. Our guide to the N260 and summary assessment covers the filing deadlines, what the statement has to show and where schedules are most often reduced. To draft one yourself, our free N260 builder fills in the official form and checks each rate against the 2026 guideline hourly rates.
Settlement-Led Costs Negotiation
Clinical negligence costs can become complex quickly. A good negotiation strategy considers:
- the bill total;
- the approved budget;
- incurred costs;
- budgeted costs;
- hourly rates;
- expert fees;
- counsel fees;
- proportionality;
- Part 36 risk;
- detailed assessment risk;
- likely recovery;
- commercial settlement value.
We help claimant firms take a realistic but firm approach to recovery. The aim is not to argue every point for the sake of it. The aim is to recover the best commercial outcome for the work properly done.
Secure Client Portal
DMD Costs provides a secure client portal for solicitor firms. You can upload clinical negligence files directly into our system without using third-party transfer apps. The portal allows you to:
- upload records and costs documents securely;
- provide budgets, orders and correspondence;
- track the progress of each matter;
- see file status updates;
- reduce email attachments;
- keep everything organised in one place.
This is particularly useful for clinical negligence files, where documents can be substantial and file organisation matters.
We work for claimant firms across England and Wales, including a firm in London. Files, papers and bills are exchanged electronically, so where your firm is based makes no difference to the work.
Flexible Instructions
You can use DMD Costs whenever required. There is no need to commit to sending every clinical negligence file. You can instruct us on:
- one costs budget;
- one bill of costs;
- a Precedent S;
- a batch of files;
- overflow work;
- urgent N260s;
- PoDs and Replies;
- budget variation support;
- detailed assessment preparation.
We work flexibly around your firm’s needs.
Fixed Fee Agreed Before Instructions
Our fee is fixed and agreed before we start work.
Unless we agree otherwise in writing, our agreed fee is payable when your firm receives the recovered costs from the paying party. This gives claimant firms cost certainty and a practical payment structure.
Why Choose DMD Costs for Clinical Negligence Costs?
Clinical negligence costs require accuracy, judgement and careful presentation. DMD Costs helps claimant firms protect recovery by preparing costs documents that are clear, structured and commercially focused. We focus on:
- Precedent H budgets;
- realistic assumptions;
- phase-by-phase analysis;
- expert fee presentation;
- accurate bills of costs;
- clean Precedent S drafting;
- proportionality arguments;
- rate and grade disputes;
- Points of Dispute and Replies;
- settlement-led negotiation;
- fixed-fee certainty;
- secure portal upload and tracking.
Clinical Negligence Costs Lawyers or Costs Draftspersons?
Costs Lawyer is a regulated title, and Costs Lawyers have rights of audience. DMD Costs is a firm of law costs draftsmen, not Costs Lawyers, and we do not describe ourselves as one. Everything short of a contested hearing is work either can do: Precedent H budgets, bills of costs and Precedent S electronic bills, Points of Dispute and Replies, and negotiation to settlement. That is the work we do, for the instructing solicitor, who keeps conduct of the matter. If a bill goes to a contested hearing, we arrange the advocate (counsel or a Costs Lawyer) and prepare the papers. Here is how a costs draftsman differs from a Costs Lawyer.
Senior Technical Review
Clinical negligence costs work at DMD Costs is subject to senior technical review by Diellza Nika Hyseni, law costs draftsperson and Managing Director, who has more than 15 years’ experience of clinical negligence costs. Her files have ranged from claims worth a few thousand pounds to multi-million-pound claims, so the budget, the bill and the negotiation are pitched to the value and complexity of the case in front of her.
Our technical guidance on this area includes clinical negligence costs budgets and the CCMC and Precedent S and the electronic bill and what NHS Resolution’s 2025/26 figures mean for claimant firms.
We also write up the decisions that change how a clinical bill is drawn. The most recent is JBX v Frimley, where a claimant who lost the principal issue at an eight-day trial still recovered 85% of his costs, because failed issues, costs causation and Part 36 have to be analysed separately. Before that, HD v North Devon Healthcare Trust, where unenforceable retainers took six detailed assessments to nil and £92,000 already paid on account had to be repaid — a reminder that the first item on a bill is the liability behind it.
Clinical negligence costs are expert-heavy and procedurally awkward, and the two questions that decide recovery — whether the claim is costs-managed at all, and how the bill is drawn — are answered differently here than in most claim types. Our published guidance on both is written from the rules themselves rather than summarised from secondary sources.
We do not publish case results we have not produced: every figure on this site comes from matters this practice handled. Across our settled files, average recovery is above 70% of the bill as drafted. Beyond that, what we offer as evidence is the experience behind the work, senior review of every clinical file, and technical guidance you can check against the rules yourself.